Assess
IPSS symptom score, uroflowmetry, post-void residual, PSA, prostate ultrasound or MRI and sometimes cystoscopy establish whether laser surgery is the right option and which one.
Laser surgery for an enlarged prostate
This site explains the laser options for an enlarged prostate (benign prostatic hyperplasia, BPH), with a clear comparison against the non-laser alternatives. The central procedure, Holmium Laser Enucleation of the Prostate (HoLEP), works for almost any prostate size and can be offered to many men on blood thinners. Dr Raji Kooner has performed more than 3,000 HoLEP procedures at St Vincent's Private and Mater Hospital North Sydney.
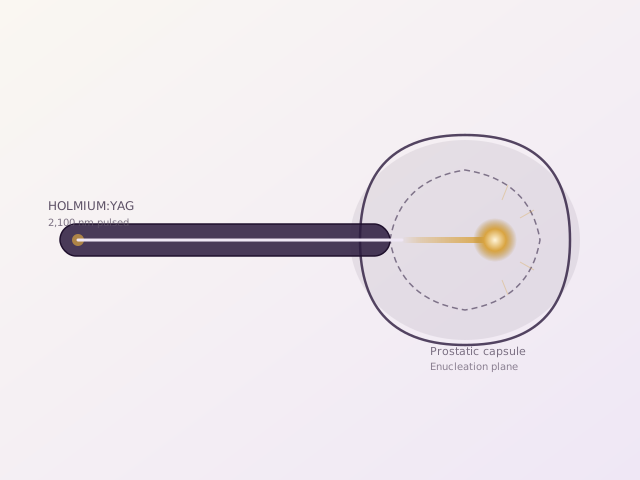
Laser surgery for the prostate uses light energy to vaporise or separate (enucleate) the obstructing tissue through a cystoscope, without an external incision. Different lasers, different targets, different strengths - but all aim to relieve the blockage while minimising bleeding and shortening catheter time compared with classical electrosurgery.
HoLEP is offered for prostates from around 30 cc up to well over 300 cc. Very large glands that previously required open surgery can often be treated endoscopically.6
Holmium and GreenLight energy seal small vessels as they cut or vaporise. Many men on aspirin, warfarin or direct oral anticoagulants can have HoLEP with their blood thinners continued where clinically appropriate.12, 13
Because the obstructing adenoma is enucleated rather than shaved, retreatment rates after HoLEP are very low: one major registry of 33,000 patients reported only 1.4% re-operation at seven years.18
No single laser suits every prostate. The device and technique are chosen based on prostate size, bladder condition, blood-thinner status and symptom pattern.
Holmium Laser Enucleation of the Prostate. The flagship procedure - suitable for any size gland, including very large prostates and patients on anticoagulants.
Photoselective vaporisation with the 532 nm KTP (GreenLight) laser. Well suited to small and medium prostates where enucleation is not needed.
Holmium Laser Incision of the Bladder Neck. A short targeted procedure for a tight bladder neck in small prostates or after previous surgery.
Thulium fibre (or Tm:YAG) laser enucleation - an emerging alternative with a continuous-wave beam and a shallower depth of penetration.
IPSS symptom score, uroflowmetry, post-void residual, PSA, prostate ultrasound or MRI and sometimes cystoscopy establish whether laser surgery is the right option and which one.
Under general or spinal anaesthesia, a laser fibre separates the obstructing adenoma from the surgical capsule in one or three lobes. The tissue is then morcellated in the bladder and sent to pathology.
A urinary catheter drains the bladder overnight while haematuria clears. Most men go home the following morning.
Catheter usually removed on day 1. Urinary urgency settles over the first two to six weeks. Return to office work within a week; heavy manual work after 4-6 weeks.
Laser is one part of a wider treatment menu. Short comparison pages for each non-laser option are linked below, and a full comparison matrix sits on the alternatives hub.
| Option | Mechanism | Tissue removed? | Size limit | Hospital stay |
|---|---|---|---|---|
| HoLEP | Holmium laser enucleation of the adenoma. | Yes, sent to pathology. | None in practice. | Usually overnight. |
| GreenLight | KTP laser photoselective vaporisation. | Vaporised. | Small to medium glands. | Usually day surgery. |
| TURP | Electrosurgical resection. | Yes, sent to pathology. | Best for small-medium glands. | Usually overnight. |
| UroLift | Permanent tethers hold lobes apart. | No. | Small-medium, no median lobe. | Day surgery. |
| Rezum | Water vapour ablation. | Reabsorbed by the body. | Small-medium. | Day surgery. |
| iTind | Temporary nitinol device reshapes urethra. | No. | Small-medium, no median lobe. | Day surgery. |
| Aquablation | Robotic-controlled high-velocity saline jet. | Yes. | Most sizes. | Usually overnight. |
| Open prostatectomy | Open surgical enucleation. | Yes. | Very large glands historically. | Several days. |
Each short comparison page finishes with a "vs HoLEP" summary so you can quickly see where a laser and a non-laser option trade off. Booking for non-laser options links through to urologynsw.com.au or itind.com.au.
Dr Kooner is a senior Sydney urologist who has been offering Holmium laser for the prostate for more than two decades. With over 3,000 HoLEP procedures completed at St Vincent's Private and Mater Hospital North Sydney, he is one of the most experienced HoLEP surgeons in Australia. His HoLEP work is recognised by a formal Certificate of Achievement on display in the rooms.
Clinical care, referrals and the wider range of urological services are provided through Urology NSW. A full curriculum vitae, publications list and media record sit on rajikooner.com.au.
Suite 1303, Level 13
St Vincent's Private Hospital
406 Victoria Street
Darlinghurst NSW 2010
Suite 1.12, Level 1
3-9 Gillies Street
North Sydney NSW 2060
Suite 9, 70 Bowral Street
Bowral NSW 2576
You can ask for a second opinion on your symptoms, flow studies and prostate size before deciding between medication, HoLEP, GreenLight, TURP, UroLift, Rezum or iTind.